
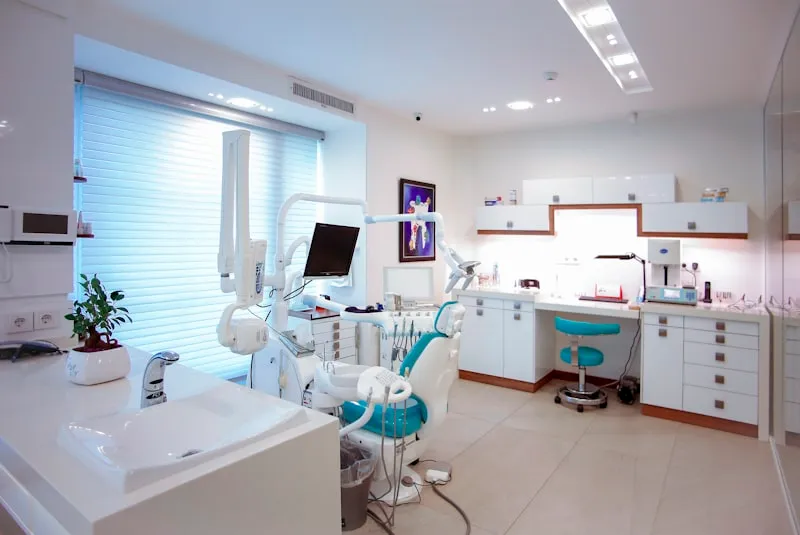
Dental Office Cleaning in Marlborough, MA
Clinical-grade cleaning for dental practices in Marlborough and across Middlesex County. Founded by a 22-year clinical veteran. $2M insured.
What dental office cleaning covers in Marlborough
For dental practices in Marlborough, the risk we plan around is procedural aerosol and waterline biofilm. The surfaces that decide the outcome: operatory surfaces, suction lines, sterilisation area clean/dirty divide.
Facility types we clean under this service:
- General Dentistry
- Orthodontics
- Oral Surgery
- Periodontics
Usually arranged with the office manager / practice-owner dentist.
Marlborough at a glance
- Municipal form: City
- County: Middlesex County
- Region: MetroWest
- Population: 41,793 (2020 U.S. Census)
- Land area: 20.9 sq mi
- Water area: 1.2 sq mi
- Density: about 2,003 residents per sq mi
- ZIP code: 01752
- From our base: Marlborough is our home base
- Typical healthcare setting: community acute care hospital campus with a surrounding cluster of independent medical and specialty offices
Marlborough settings that match this service include Paglia Family Dental (general dental practice); Metrowest Dental Center (general dental practice). They are listed as market context — the kind of dental practice our protocol is written for — not as clients.
Medical offices in Marlborough cluster along Union Street.
Local health authority: Marlborough Board of Health (official Marlborough page). Healthcare facilities are licensed and surveyed by the Massachusetts Department of Public Health; the local board handles environmental-health matters under the State Sanitary Code and local rules.
Sources: U.S. Census Bureau (2020 Census; Gazetteer files), USPS ZIP codes, and our own verification of local facilities. Distances are straight-line.
How we clean dental practices in Marlborough
High-touch surfaces on every visit
- Dental chair controls and headrest
- Operatory light handles
- Delivery unit, tray and bracket table
- X-ray tube head and sensor holder
- Waiting-room chair arms
- Restroom fixtures
What the crew does, in order
- Clean housekeeping surfaces — floors, walls, counters outside the operatory field — with an EPA-registered disinfectant.
- Leave dental unit waterlines, suction traps and instrument reprocessing to trained clinical staff.
- Empty general trash; amalgam, sharps and regulated waste stay with your licensed hauler.
- Damp-mop operatory floors, working from the back of the room toward the door.
- Log each operatory, the products used and anything that needs the practice's attention.
A starting schedule
- Floors: daily in operatories and the sterilization area.
- Waiting room and restrooms: daily, with high-touch points more often in busy practices.
- Walls, vents and cabinet exteriors: periodically or when visibly soiled.
Practices with Saturday hours usually need a weekend visit or an early Monday clean.
Documentation you receive
- Operatory-by-operatory cleaning checklist
- Product list with EPA registration numbers and contact times
- Service logs signed each visit
- Certificate of insurance naming the practice
What inspectors cite — and how we prevent it
Real, published regulatory findings — every citation links to its source.
CDC Summary of Infection Prevention Practices in Dental Settings (2016), Environmental Infection Prevention and Control
Surface barriers on hard-to-clean clinical contact surfaces — chair switches, light handles, computer equipment — not changed between patients, or the surface underneath never checked for soiling once the barrier comes off.
CDC Summary of Infection Prevention Practices in Dental Settings (2016)
Non-barrier-protected clinical contact surfaces not cleaned and disinfected with an EPA-registered hospital disinfectant after each patient.
CDC Best Practices for Environmental Infection Prevention and Control, Dental — clinical contact surfaces
A low-level disinfectant used where blood contamination is visible. Blood-contaminated clinical contact surfaces require an EPA-registered intermediate-level disinfectant with a tuberculocidal claim.
Questions worth asking at the walkthrough
- How will your crew keep the clean and dirty sides of our sterilization area separate?
- What will you never touch in the operatory?
- How do you handle an aerosol-heavy day in terms of end-of-day cleaning?
We answer each of these in writing after the free assessment.
Marlborough questions, answered
Yes. Marlborough (Middlesex County) is one of the 109 Massachusetts cities and towns we serve. Every engagement starts with a free on-site assessment; call (978) 307-8107.
All of them: 01752. If your facility sits on a town line, tell us the street address and we will confirm.
The Marlborough Board of Health; its official page is https://www.marlborough-ma.gov/370/Board-of-Health. Clinics, hospitals and long-term care facilities are licensed and surveyed by the Massachusetts Department of Public Health, while the local board of health handles local environmental-health matters under the State Sanitary Code and local regulations. Our cleaning records are kept so they serve both.
Yes. A low-level disinfectant is not adequate where blood contamination is visible. CDC best practice for dental clinical contact surfaces calls for an EPA-registered intermediate-level disinfectant with a tuberculocidal claim in that situation, and the organic soil must be cleaned off before the disinfectant is applied, because organic matter inactivates many products. Our crews carry both levels and are trained on when to escalate. If the blood is fresh and the operatory is in use, it is your staff's job rather than ours, because it should not wait for our visit.
The Board sets infection control requirements at 234 CMR 5.05. 234 CMR 5.05(1) requires compliance with the CDC dental infection control guidelines, and 234 CMR 5.05(2) carries the OSHA Bloodborne Pathogens Standard, 29 CFR 1910.1030, into the dental practice framework. So the written cleaning schedule at 29 CFR 1910.1030(d)(4)(i) is not only a federal obligation, it is a licensure-side expectation as well. Practically, that means one documentation set answers both the OSHA question and the Board question without maintaining two parallel binders.
It is one of the most common issues we correct. The CDC dental guidance is explicit about following manufacturer instructions for amount, dilution, contact time, and safe use and disposal, and some products must be made up fresh daily. A wrong dilution, an expired container, a solution stored in heat or light, or a wipe that dries before the label kill time all mean the surface was not actually disinfected. We standardize on ready-to-use products where the surface allows, date-mark anything that is mixed, and keep labels accessible in the operatory area.
Neighboring towns we serve
Free dental office cleaning assessment in Marlborough
22+ years clinical experience. $2M insured. No obligation.