
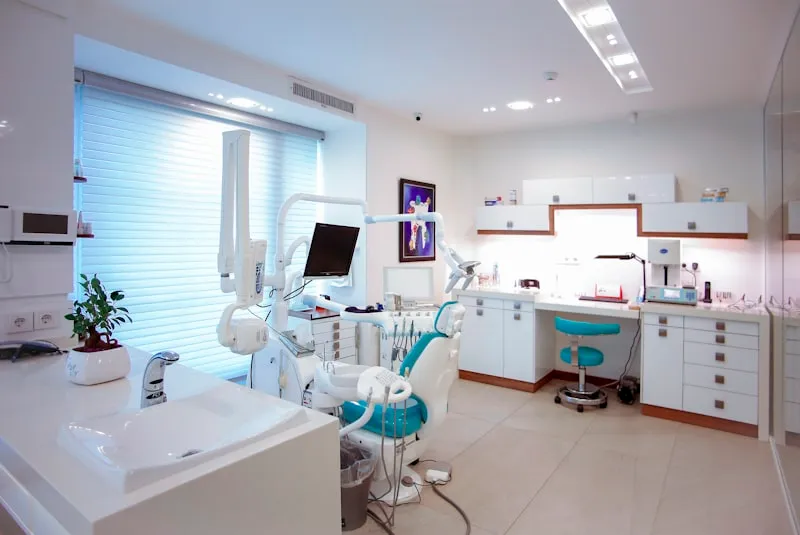
Dental Office Cleaning in Melrose, MA
Serving Melrose from our Marlborough base, about 26 miles east. Written scope, EPA-registered products, signed logs.
Dental Office Cleaning for Melrose facilities
For dental practices in Melrose, the risk we plan around is procedural aerosol and waterline biofilm. The surfaces that decide the outcome: operatory surfaces, suction lines, sterilisation area clean/dirty divide.
Facility types we clean under this service:
- General Dentistry
- Orthodontics
- Oral Surgery
- Periodontics
Usually arranged with the office manager / practice-owner dentist.
About Melrose, MA
- Municipal form: City
- County: Middlesex County
- Region: Greater Boston
- Population: 29,817 (2020 U.S. Census)
- Land area: 4.7 sq mi
- Water area: 0.1 sq mi
- Density: about 6,367 residents per sq mi
- ZIP code: 02176
- From our base: about 26 miles east of Marlborough (straight line)
- Typical healthcare setting: community teaching hospital campus
Melrose settings that match this service include Pan Dental Care (general dental practice); Melrose Family Dentistry (general dental practice). They are listed as market context — the kind of dental practice our protocol is written for — not as clients.
Local health authority: Melrose Health & Human Services (official Melrose page). Healthcare facilities are licensed and surveyed by the Massachusetts Department of Public Health; the local board handles environmental-health matters under the State Sanitary Code and local rules.
Sources: U.S. Census Bureau (2020 Census; Gazetteer files), USPS ZIP codes, and our own verification of local facilities. Distances are straight-line.
Citations Melrose dental practices can avoid
Real, published regulatory findings — every citation links to its source.
CDC Summary of Infection Prevention Practices in Dental Settings (2016), Environmental Infection Prevention and Control
No written policies and procedures for routine cleaning and disinfection of environmental surfaces as part of the practice's infection prevention plan.
CDC Summary of Infection Prevention Practices in Dental Settings (2016), Environmental Infection Prevention and Control
Surface barriers on hard-to-clean clinical contact surfaces — chair switches, light handles, computer equipment — not changed between patients, or the surface underneath never checked for soiling once the barrier comes off.
CDC Summary of Infection Prevention Practices in Dental Settings (2016)
Non-barrier-protected clinical contact surfaces not cleaned and disinfected with an EPA-registered hospital disinfectant after each patient.
How we clean dental practices in Melrose
High-touch surfaces on every visit
- Keyboards and mice in each operatory
- Cabinet and drawer pulls
- Sterilization-area counters on the clean side
- Front-desk counter and payment terminal
- Waiting-room chair arms
- Restroom fixtures
How a visit runs
- Confirm which clinical contact surfaces and barriers your dental assistants handle between patients.
- Keep the sterilization area's clean and dirty sides separate: separate cloths, clean side first, never back again.
- Clean housekeeping surfaces — floors, walls, counters outside the operatory field — with an EPA-registered disinfectant.
- Wipe operatory surfaces that are not barrier-protected at end of day, following the practice's product choice.
- Empty general trash; amalgam, sharps and regulated waste stay with your licensed hauler.
Frequency, area by area
- Clinical contact surfaces: between patients by the dental team (or barrier change).
- Operatories and sterilization area housekeeping surfaces: daily after the last patient.
- Floors: daily in operatories and the sterilization area.
Dental offices are almost always cleaned after the last patient so the end-of-day clean reflects that day's aerosol exposure.
What you keep on file
- Operatory-by-operatory cleaning checklist
- Product list with EPA registration numbers and contact times
- Safety Data Sheets for every product
- Service logs signed each visit
Before you sign with a cleaning company
- How will your crew keep the clean and dirty sides of our sterilization area separate?
- Which products will you use near our dental equipment finishes?
- How do you handle an aerosol-heavy day in terms of end-of-day cleaning?
We answer each of these in writing after the free assessment.
Melrose questions, answered
Verified examples include Pan Dental Care (general dental practice); Melrose Family Dentistry (general dental practice). We list them as local market context; they are not presented as our clients.
The Melrose Health & Human Services; its official page is https://www.cityofmelrose.org/201/Health-Human-Services. Clinics, hospitals and long-term care facilities are licensed and surveyed by the Massachusetts Department of Public Health, while the local board of health handles local environmental-health matters under the State Sanitary Code and local regulations. Our cleaning records are kept so they serve both.
The closest served towns to Melrose are Malden (about 1.8 mi), Stoneham (about 2.3 mi), Saugus (about 2.5 mi). See the full list on our service areas page.
It changes the surface list, not just the frequency. Spatter and aerosol settle well beyond the immediate chairside zone, so our end-of-day pass covers horizontal surfaces at and above chair height, cabinet fronts, light arms, the sides and base of the unit, and the floor around the chair, not only the counters your team wipes between patients. The CDC Summary of Infection Prevention Practices in Dental Settings (2016) expects routine environmental cleaning and disinfection to be set out in written policies and procedures; the surface list becomes part of yours.
The Board sets infection control requirements at 234 CMR 5.05. 234 CMR 5.05(1) requires compliance with the CDC dental infection control guidelines, and 234 CMR 5.05(2) carries the OSHA Bloodborne Pathogens Standard, 29 CFR 1910.1030, into the dental practice framework. So the written cleaning schedule at 29 CFR 1910.1030(d)(4)(i) is not only a federal obligation, it is a licensure-side expectation as well. Practically, that means one documentation set answers both the OSHA question and the Board question without maintaining two parallel binders.
It is one of the most common issues we correct. The CDC dental guidance is explicit about following manufacturer instructions for amount, dilution, contact time, and safe use and disposal, and some products must be made up fresh daily. A wrong dilution, an expired container, a solution stored in heat or light, or a wipe that dries before the label kill time all mean the surface was not actually disinfected. We standardize on ready-to-use products where the surface allows, date-mark anything that is mixed, and keep labels accessible in the operatory area.
Neighbouring towns we serve
Free dental office cleaning assessment in Melrose
22+ years clinical experience. $2M insured. No obligation.