
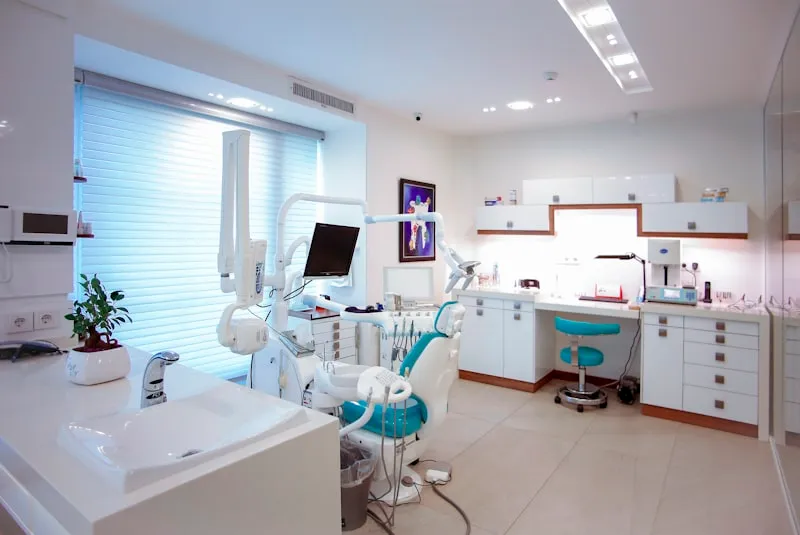
Dental Office Cleaning in Medfield, MA
Clinical-grade cleaning for dental practices in Medfield and across Norfolk County. Founded by a 22-year clinical veteran. $2M insured.
Dental Office Cleaning for Medfield facilities
For dental practices in Medfield, the risk we plan around is procedural aerosol and waterline biofilm. The surfaces that decide the outcome: operatory surfaces, suction lines, sterilisation area clean/dirty divide.
Facility types we clean under this service:
- General Dentistry
- Orthodontics
- Oral Surgery
- Periodontics
Usually arranged with the office manager / practice-owner dentist.
Medfield at a glance
- Municipal form: Town
- County: Norfolk County
- Region: MetroWest
- Population: 12,799 (2020 U.S. Census)
- Land area: 14.4 sq mi
- Water area: 0.2 sq mi
- Density: about 889 residents per sq mi
- ZIP code: 02052
- From our base: about 17 miles southeast of Marlborough (straight line)
- Typical healthcare setting: skilled nursing and rehabilitation
Medfield settings that match this service include Mary C. DeMello, DMD, PC (general dental practice); West Mill Smiles (general dental practice). They are listed as market context — the kind of dental practice our protocol is written for — not as clients.
Local health authority: Medfield Board of Health (official Medfield page). Healthcare facilities are licensed and surveyed by the Massachusetts Department of Public Health; the local board handles environmental-health matters under the State Sanitary Code and local rules.
Sources: U.S. Census Bureau (2020 Census; Gazetteer files), USPS ZIP codes, and our own verification of local facilities. Distances are straight-line.
Dental Office Cleaning in Medfield: the working detail
Where contamination concentrates
- Dental chair controls and headrest
- Operatory light handles
- Delivery unit, tray and bracket table
- X-ray tube head and sensor holder
- Sterilization-area counters on the clean side
- Front-desk counter and payment terminal
What the crew does, in order
- Clean housekeeping surfaces — floors, walls, counters outside the operatory field — with an EPA-registered disinfectant.
- Leave dental unit waterlines, suction traps and instrument reprocessing to trained clinical staff.
- Empty general trash; amalgam, sharps and regulated waste stay with your licensed hauler.
- Damp-mop operatory floors, working from the back of the room toward the door.
- Log each operatory, the products used and anything that needs the practice's attention.
Frequency, area by area
- Floors: daily in operatories and the sterilization area.
- Waiting room and restrooms: daily, with high-touch points more often in busy practices.
- Walls, vents and cabinet exteriors: periodically or when visibly soiled.
Practices with Saturday hours usually need a weekend visit or an early Monday clean.
What you keep on file
- Operatory-by-operatory cleaning checklist
- Product list with EPA registration numbers and contact times
- Service logs signed each visit
- Certificate of insurance naming the practice
Citations Medfield dental practices can avoid
Real, published regulatory findings — every citation links to its source.
CDC Summary of Infection Prevention Practices in Dental Settings (2016), Environmental Infection Prevention and Control
Surface barriers on hard-to-clean clinical contact surfaces — chair switches, light handles, computer equipment — not changed between patients, or the surface underneath never checked for soiling once the barrier comes off.
CDC Summary of Infection Prevention Practices in Dental Settings (2016)
Non-barrier-protected clinical contact surfaces not cleaned and disinfected with an EPA-registered hospital disinfectant after each patient.
CDC Best Practices for Environmental Infection Prevention and Control, Dental — clinical contact surfaces
A low-level disinfectant used where blood contamination is visible. Blood-contaminated clinical contact surfaces require an EPA-registered intermediate-level disinfectant with a tuberculocidal claim.
Questions to ask any Medfield cleaning vendor
- How will your crew keep the clean and dirty sides of our sterilization area separate?
- What will you never touch in the operatory?
- How do you handle an aerosol-heavy day in terms of end-of-day cleaning?
We answer each of these in writing after the free assessment.
Medfield questions, answered
Verified examples include Mary C. DeMello, DMD, PC (general dental practice); West Mill Smiles (general dental practice). We list them as local market context; they are not presented as our clients.
The Medfield Board of Health; its official page is https://www.town.medfield.net/269/Board-of-Health. Clinics, hospitals and long-term care facilities are licensed and surveyed by the Massachusetts Department of Public Health, while the local board of health handles local environmental-health matters under the State Sanitary Code and local regulations. Our cleaning records are kept so they serve both.
The closest served towns to Medfield are Millis (about 3.1 mi), Dover (about 3.5 mi), Walpole (about 3.7 mi). See the full list on our service areas page.
No. Surface barriers on clinical contact surfaces are changed between patients by the clinical team, and the surface underneath is checked for soiling when the barrier comes off. That is a between-patient task in an occupied operatory, described in the CDC Summary of Infection Prevention Practices in Dental Settings (2016) under environmental infection prevention and control. Our crews arrive when the operatories are empty. What we can do is confirm barriers are in place at the start of the day and clean and disinfect the surfaces beneath them on the end-of-day pass.
No. Evacuation line cleaning and trap changes are clinical equipment maintenance, performed to the line cleaner manufacturer's instructions by your staff, and the wrong chemistry in those lines can damage the unit. We do not open traps or introduce anything into the lines. We clean the surrounding cabinetry, the sink, and the floor beneath, and we will report a trap that is visibly overdue or a line cleaner container that has run empty, so it gets attention rather than being missed until the next scheduled maintenance.
Segregation at the point of generation is your clinical team's, and it happens before we arrive. Blood-soaked gauze and extracted teeth belong in a leak-resistant biohazard container rather than ordinary trash, and sharps belong in a labeled puncture-resistant container, consistent with CDC dental waste guidance and 29 CFR 1910.1030(d)(4)(iii). Our crews handle general waste only. If we find regulated waste in a general trash receptacle, we do not sort it. We stop, leave it, and report it, because handling it would create an exposure risk for our staff.
Nearby dental practices we clean
Free dental office cleaning assessment in Medfield
22+ years clinical experience. $2M insured. No obligation.