
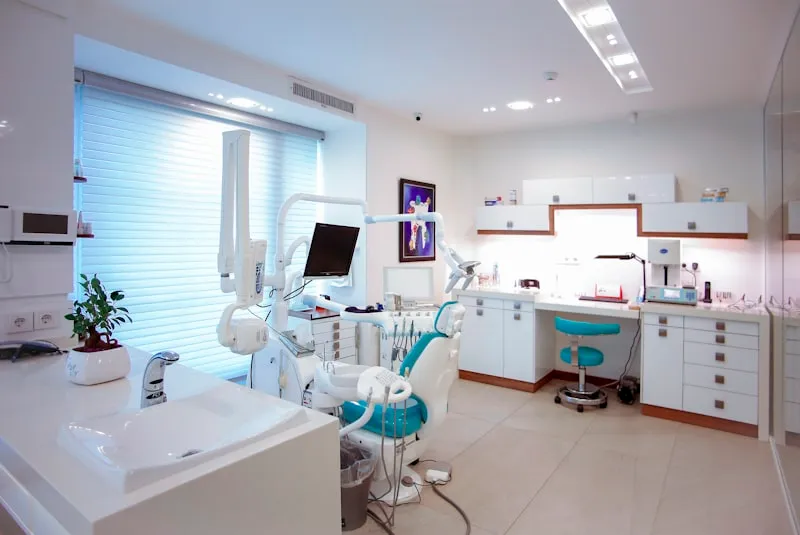
Dental Office Cleaning in Millis, MA
Dental practice cleaning built on CDC guidance, documented visit by visit, for Millis facilities. $2M insured.
Dental Office Cleaning for Millis facilities
In a dental practice, most cleaning failures happen at operatory surfaces, suction lines, sterilisation area clean/dirty divide. That is where our Millis crews start, because the underlying risk is procedural aerosol and waterline biofilm.
Facility types we clean under this service:
- General Dentistry
- Orthodontics
- Oral Surgery
- Periodontics
Usually arranged with the office manager / practice-owner dentist.
About Millis, MA
- Municipal form: Town
- County: Norfolk County
- Region: MetroWest
- Population: 8,460 (2020 U.S. Census)
- Land area: 12.0 sq mi
- Water area: 0.2 sq mi
- Density: about 703 residents per sq mi
- ZIP code: 02054
- From our base: about 15 miles southeast of Marlborough (straight line)
- Typical healthcare setting: senior living and residential care
Millis settings that match this service include Main Street Dental (general dental practice); Pleasant Dental (general dental practice). They are listed as market context — the kind of dental practice our protocol is written for — not as clients.
Local health authority: Millis Board of Health (official Millis page). Healthcare facilities are licensed and surveyed by the Massachusetts Department of Public Health; the local board handles environmental-health matters under the State Sanitary Code and local rules.
Sources: U.S. Census Bureau (2020 Census; Gazetteer files), USPS ZIP codes, and our own verification of local facilities. Distances are straight-line.
Dental Office Cleaning in Millis: the working detail
Where contamination concentrates
- Keyboards and mice in each operatory
- Cabinet and drawer pulls
- Sterilization-area counters on the clean side
- Front-desk counter and payment terminal
- Waiting-room chair arms
- Restroom fixtures
What the crew does, in order
- Confirm which clinical contact surfaces and barriers your dental assistants handle between patients.
- Keep the sterilization area's clean and dirty sides separate: separate cloths, clean side first, never back again.
- Clean housekeeping surfaces — floors, walls, counters outside the operatory field — with an EPA-registered disinfectant.
- Wipe operatory surfaces that are not barrier-protected at end of day, following the practice's product choice.
- Damp-mop operatory floors, working from the back of the room toward the door.
Frequency, area by area
- Operatories and sterilization area housekeeping surfaces: daily after the last patient.
- Floors: daily in operatories and the sterilization area.
- Waiting room and restrooms: daily, with high-touch points more often in busy practices.
Practices with Saturday hours usually need a weekend visit or an early Monday clean.
What you keep on file
- Operatory-by-operatory cleaning checklist
- Product list with EPA registration numbers and contact times
- Safety Data Sheets for every product
- Service logs signed each visit
What inspectors cite — and how we prevent it
Real, published regulatory findings — every citation links to its source.
CDC Best Practices, disposing of medical waste; OSHA 29 CFR 1910.1030(d)(4)(iii)
Regulated medical waste not segregated or contained correctly — blood-soaked gauze and extracted teeth in ordinary trash rather than a leak-resistant biohazard bag, sharps outside a labelled puncture-resistant container.
CDC Summary of Infection Prevention Practices in Dental Settings (2016), Dental Unit Water Quality
Dental treatment water not maintained to drinking-water quality of 500 CFU/mL or fewer, or waterline treatment and monitoring not performed to the manufacturer's schedule. Independent water bottles alone are not sufficient.
29 CFR 1910.1030(d)(4)(i); Massachusetts adopts this at 234 CMR 5.05(2), and 234 CMR 5.05(1) requires compliance with the CDC dental infection control guidelines
No written schedule for cleaning and method of decontamination determined and implemented for the practice.
Before you sign with a cleaning company
- What will you never touch in the operatory?
- What logs will we have for a Board of Registration in Dentistry inspection?
- Who holds bloodborne pathogen training on your crew?
We answer each of these in writing after the free assessment.
FAQ: dental office cleaning in Millis
All of them: 02054. If your facility sits on a town line, tell us the street address and we will confirm.
Verified examples include Main Street Dental (general dental practice); Pleasant Dental (general dental practice). We list them as local market context; they are not presented as our clients.
The Millis Board of Health; its official page is https://www.millisma.gov/board-health. Clinics, hospitals and long-term care facilities are licensed and surveyed by the Massachusetts Department of Public Health, while the local board of health handles local environmental-health matters under the State Sanitary Code and local regulations. Our cleaning records are kept so they serve both.
No. Surface barriers on clinical contact surfaces are changed between patients by the clinical team, and the surface underneath is checked for soiling when the barrier comes off. That is a between-patient task in an occupied operatory, described in the CDC Summary of Infection Prevention Practices in Dental Settings (2016) under environmental infection prevention and control. Our crews arrive when the operatories are empty. What we can do is confirm barriers are in place at the start of the day and clean and disinfect the surfaces beneath them on the end-of-day pass.
The Board sets infection control requirements at 234 CMR 5.05. 234 CMR 5.05(1) requires compliance with the CDC dental infection control guidelines, and 234 CMR 5.05(2) carries the OSHA Bloodborne Pathogens Standard, 29 CFR 1910.1030, into the dental practice framework. So the written cleaning schedule at 29 CFR 1910.1030(d)(4)(i) is not only a federal obligation, it is a licensure-side expectation as well. Practically, that means one documentation set answers both the OSHA question and the Board question without maintaining two parallel binders.
It is one of the most common issues we correct. The CDC dental guidance is explicit about following manufacturer instructions for amount, dilution, contact time, and safe use and disposal, and some products must be made up fresh daily. A wrong dilution, an expired container, a solution stored in heat or light, or a wipe that dries before the label kill time all mean the surface was not actually disinfected. We standardize on ready-to-use products where the surface allows, date-mark anything that is mixed, and keep labels accessible in the operatory area.
Nearby dental practices we clean
Free dental office cleaning assessment in Millis
22+ years clinical experience. $2M insured. No obligation.